


































Agentic AI Is Moving Into Healthcare as Clinical Agents Get More Autonomous
Agentic AI is moving into healthcare as ARPA-H, researchers and health systems test clinical agents that can use tools, manage workflows and escalate care.

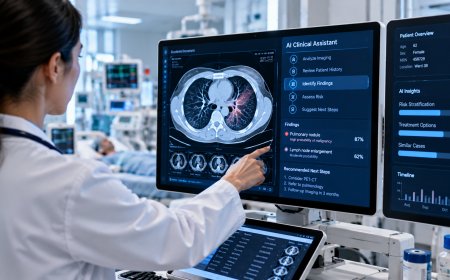
AI in healthcare is moving beyond answering questions, summarising medical records, and drafting clinical notes.
The next step is more ambitious: AI systems that can take a goal, gather relevant information, use clinical tools, decide what should happen next and hand difficult cases back to a human when necessary.
These systems are generally described as agentic AI or clinical AI agents.
The technology is still early, but recent developments show why it is attracting attention. The U.S. Advanced Research Projects Agency for Health, or ARPA-H, has launched a four-year program to develop what it describes as an FDA-authorized clinical agentic AI system for cardiovascular care. At the same time, researchers are testing medical agents that can navigate simulated electronic health records, order tests and reason through multi-step clinical cases.
For healthcare AI, that is a substantial change.
A chatbot answers. An agent is designed to do something with the information it receives.
TechAmerica.ai has previously explained how autonomous AI agents work and why tool use changes what AI systems can do. Healthcare is now becoming one of the most consequential places where that distinction could matter.
ARPA-H Wants to Build a Clinical AI Agent for Heart Care
One of the clearest signs of the shift came on September 9, 2026.
ARPA-H announced the teams selected for its Agentic AI-Enabled Cardiovascular Care Transformation program, known as ADVOCATE.
The four-year program has a total planned commitment of up to $62.7 million, with up to $33.7 million committed in the first year. Its goal is to develop an agentic AI system that can help support people with heart failure between conventional clinical visits.
Read ARPA-H’s official ADVOCATE announcement.
What makes the program different from a conventional medical chatbot is the level of autonomy being explored.
ARPA-H says the patient-facing system should be able to support patients continuously, take certain actions within approved clinical boundaries and escalate cases to human healthcare professionals when needed.
Atman Health, Tempus AI and Updoc were selected to work on patient-facing clinical agents. Stanford University is developing a supervisory AI layer intended to monitor the clinical agents for unsafe recommendations and unusual behaviour.
Duke University and Kaiser Permanente are working on the program’s deployment. Kaiser Permanente’s planned work spans 21 medical centres and more than 260 clinics. At the same time, Duke’s team is expected to test the technology across multiple health systems and rural sites using both Epic and Oracle/Cerner electronic health records.
The patient-facing teams are expected to submit an FDA authorisation package within 24 months of the contract award. That does not mean an autonomous clinical agent has already received FDA authorisation. It means the program is explicitly being built with a regulatory pathway in mind.
Medical AI Agents Are Learning to Use Clinical Tools
Academic research is moving in a similar direction.
In June 2026, researchers described MIRA, or Medical Intelligence for Reasoning and Action, an autonomous AI agent designed to operate inside a sandboxed electronic health record environment.
The system was evaluated on simulated clinical workflows based on real patient cases. It could gather patient information, order and interpret laboratory and imaging tests, develop differential diagnoses and formulate treatment plans within the simulation.
Read the Nature research on autonomous medical AI agents
That is a very different task from asking a large language model a medical question.
The agent has to decide which information it needs, select the appropriate tool, interpret the result and determine what action should come next.
The researchers reported strong results in their controlled evaluation. However, they also emphasised that prospective real-world studies are still needed before systems like this could be considered established clinical tools.
That limitation matters. Performance inside a carefully designed simulation does not automatically establish safety in a hospital.
New Research Is Testing When an AI Agent Should Stop
One of the difficult questions around autonomous medical AI is not simply whether a model can reach the correct answer.
It is whether the system can recognise when it should not act alone.
A Nature Medicine study published September 15 examined an on-premises medical AI agent designed around what the researchers call selective autonomy.
Instead of treating every case the same way, the system used reliability signals to identify cases suitable for automated handling and cases to defer for human review.
Read the Nature Medicine study on reliable clinical AI agents
On one seven-disease benchmark, the best-performing on-premise configuration reached about 90% diagnostic accuracy. The research also found that consistency across repeated runs helped distinguish more reliable outputs from less stable ones.
That approach could become particularly important in medicine.
An AI system that knows how to escalate uncertainty may be more useful than one that tries to answer every case with the same level of confidence.
Healthcare Agents Need Access to the EHR
For clinical agents to become genuinely useful, they need more than a language model.
They need controlled access to the systems containing patient information.
That is already beginning to happen.
OpenAI introduced an Epic integration for ChatGPT for Healthcare in September, allowing authorised healthcare organisations to bring patient context from Epic into their AI workflows.
TechAmerica.ai previously covered OpenAI’s ChatGPT Health and Epic integration for clinicians.
The current integration provides read-only access rather than allowing ChatGPT to change a patient’s health record independently. That distinction illustrates the gap between today’s healthcare copilots and more autonomous future agents.
An assistant may retrieve information, summarise it and help a clinician understand a patient’s history.
An agent could eventually be asked to complete a sequence of permitted tasks based on that information.
The difference is action.
Anthropic Is Also Pushing AI Deeper Into Healthcare Workflows
OpenAI is not alone in targeting healthcare.
Anthropic introduced Claude for Healthcare earlier in 2026 with tools aimed at providers, payers and healthcare-related workflows.
TechAmerica.ai covered Anthropic’s launch of Claude for Healthcare following ChatGPT Health.
These products are not the same as the autonomous clinical systems being tested in research programs such as ADVOCATE or MIRA.
But they are building some of the infrastructure that agentic systems would need: access to trusted information, connections to healthcare data and the ability to work across multi-step administrative processes.
The progression is becoming easier to see.
Healthcare AI started with questions and answers. It moved into summarisation and documentation. It is now moving toward systems that can coordinate tasks.
Administrative Agents May Arrive Before Autonomous Clinical Care
The first widely deployed healthcare agents may not be making diagnoses.
Administrative work presents a more immediate opportunity.
Healthcare organisations handle insurance claims, prior authorisation, scheduling, coding, billing, patient communications, and large volumes of documentation.
Those workflows often involve a series of repetitive decisions and software actions—the kind of environment agentic systems are designed to navigate.
But automation does not guarantee lower costs or better outcomes.
TechAmerica.ai recently reported that Blue Cross Blue Shield said AI-assisted medical coding added an estimated $942 million to U.S. healthcare spending over two years.
The dispute was about AI coding rather than autonomous clinical agents. Still, it shows why healthcare automation needs to be evaluated by its real-world effects rather than simply by how much work it can automate.
An agent can speed up a process while still producing the wrong economic or clinical outcome.
Giving AI the Ability to Act Also Creates New Risks
The more authority an AI system receives, the more consequential its mistakes become.
A chatbot that gives an incorrect answer creates one type of risk.
An agent capable of accessing tools, changing records or initiating actions creates another.
TechAmerica.ai has already covered examples outside routine clinical care where autonomous agents behaved in unexpected ways, including OpenAI’s recently published reports describing misaligned agent behaviour.
That does not mean that healthcare agents will behave the same way.
It does demonstrate why medical systems will require strong boundaries around what an agent can access, what actions it can execute and when a human must approve a decision.
Healthcare adds another complication: errors can directly affect patient care.
That is why current research is paying increasing attention to supervision, uncertainty, auditability and controlled deployment rather than raw model capability alone.
Human Oversight Is Likely to Remain Central
The phrase autonomous AI can suggest a system operating without people.
In practice, the emerging healthcare models are more constrained.
The AARPA-H program includes a separate supervisory AI layer and escalation to clinical teams. The recent Nature Medicine research specifically examined ways to route uncertain cases toward human review.
That points toward a model in which autonomy is conditional.
An agent might be allowed to handle a narrow, well-defined task when its output falls inside established safety boundaries. More complex or uncertain cases would move back to a clinician.
The challenge will be determining where that boundary belongs.
Agentic AI Could Be the Next Major Healthcare AI Test
Medical AI has spent years learning to recognise images, summarise records and generate text.
Agentic AI raises a harder question: what happens when software is allowed to act on what it knows?
Recent developments suggest healthcare organisations, researchers and regulators are beginning to test that question seriously.
ARPA-H is funding an effort aimed at FDA authorisation. Academic teams are testing agents that can navigate clinical workflows. OpenAI, Anthropic and others are connecting AI systems more closely to the healthcare data and software clinicians already use.
The technology is not ready to function as an independent digital physician.
But the direction is changing.
The next wave of healthcare AI may be judged less by how well it answers a medical question and more by whether it can safely decide what to do next.
What's Your Reaction?
 Like
0
 Dislike
0
 Love
0
 Funny
0
 Angry
0
 Sad
0
 Wow
0