


































Agentic AI in Healthcare Is Moving Closer to Real-World Clinical Use
ARPA-H and medical researchers are testing AI agents that can use clinical tools, navigate health records and defer uncertain decisions to clinicians.
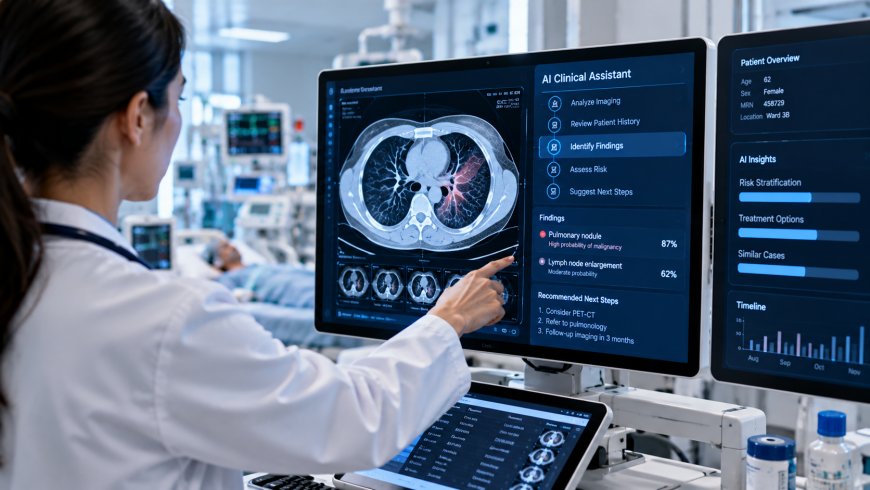
Artificial intelligence in healthcare is moving beyond systems that answer questions or generate recommendations.
Researchers and government-backed programs are now testing AI agents that can work through multi-step clinical problems, use medical tools, interact with electronic health record environments, and decide when to hand a case back to a human clinician.
The idea is usually described as agentic AI.
Unlike a conventional chatbot, an AI agent is designed to pursue a goal through a sequence of actions. In healthcare, that could mean reviewing patient information, deciding which tests are needed, interpreting the results and determining what should happen next within tightly controlled boundaries.
These systems are still early. But several developments in 2026 suggest clinical agents are moving closer to serious real-world evaluation.
For readers unfamiliar with the underlying technology, TechAmerica.ai has previously explained how AI agents can plan tasks, use tools and carry out multi-step workflows. TechAmerica.ai: What Are AI Agents?
ARPA-H Is Funding an Agentic AI System for Heart Care
One of the strongest signals came from the U.S. Advanced Research Projects Agency for Health.
On September 9, 2026, ARPA-H announced the teams selected for its AgenticAI-Enabled Cardiovascular Care Transformation program, known as ADVOCATE.
The four-year program carries a planned commitment of up to $62.7 million, including up to $33.7 million in its first year.
Its goal is unusually ambitious: develop a reliable clinical agentic AI system for cardiovascular care and pursue FDA authorisation.
The planned technology is intended to support people with heart failure between conventional appointments while escalating cases to clinical professionals when human involvement is required.
Read ARPA-H’s ADVOCATE announcement.
ARPA-H selected Atman Health, Tempus AI and Updoc to develop patient-facing clinical agents.
Stanford University is working on a supervisory agent designed to monitor the clinical systems for potentially unsafe recommendations or unusual behaviour.
Duke University and Kaiser Permanente are involved in plans for large-scale testing and deployment.
The patient-facing teams are expected to work toward an FDA authorisation submission within the program timeline.
That distinction is important. ADVOCATE is an effort to develop and validate a regulated system; it is not evidence that an autonomous cardiovascular AI agent has already received FDA authorisation.
MIRA Shows What an EHR-Integrated Medical Agent Could Do
Academic researchers are testing another version of the idea.
A study published in Nature in June described MIRA, or Medical Intelligence for Reasoning and Action, an autonomous AI agent designed to operate inside a sandboxed electronic health record environment.
Researchers gave MIRA simulated patient cases derived from real clinical data.
The agent could retrieve patient histories, order and interpret laboratory tests, request imaging and microbiology tests, generate differential diagnoses and formulate treatment plans.
It could also make structured decisions about medications, admissions, and surgical procedures within the simulated environment.
Read the Nature study on autonomous medical AI agents
This is substantially different from asking a medical language model for a diagnosis in a chat window.
The agent had to decide what information it needed, use available tools to obtain it, interpret the results, and determine its next action.
Researchers reported strong performance in the experimental setting, including results that compared favourably with physician performance on several evaluated tasks.
But the authors also made an important limitation clear: prospective real-world studies are still needed to establish generalizability, safety and governance.
In other words, MIRA demonstrates what a medical agent may be technically capable of doing inside a controlled environment. It does not establish that the system is ready to manage patients independently in a hospital.
Researchers Are Testing AI Agents That Know When to Stop
Capability is only part of the problem.
An autonomous clinical system also needs to recognise when it is uncertain.
A Nature Medicine study published on September 15, 2026 examined an on-premises clinical AI agent designed around the idea of selective autonomy.
Instead of attempting to handle every case automatically, the system used reliability measurements to separate cases that could potentially be handled autonomously from those that should be deferred for human review.
Read the Nature Medicine study on reliable clinical AI agents
Across two benchmarks derived from the MIMIC-IV clinical database, researchers reported diagnostic accuracy of 90.04% on a seven-disease task and 83.8% on a four-disease task.
One of the more interesting findings involved behavioural consistency.
Researchers repeatedly ran cases through the system and examined whether the agent arrived at stable conclusions. Consistency proved useful as a signal for identifying more reliable decisions.
At a behavioural-consistency threshold of 0.90, the system retained 49.4% of cases and achieved 98.9% diagnostic accuracy on that subset.
The implication is important.
A clinically useful AI agent may not need to handle every case.
A safer model may work autonomously only when reliability signals are strong and transfers uncertain cases to a clinician.
Another AI Agent Is Being Tested in Maternal and Infant Health
Agentic medical research is also expanding beyond general diagnostic workflows.
A Nature Medicine study published September 4 introduced MoChiAgent, an AI system designed to predict maternal and infant health outcomes using longitudinal electronic health record data.
The system orchestrates multiple tools to analyse sequential medical information, including routine laboratory results, and forecast potential maternal and infant conditions.
Read the Nature Medicine MoChiAgent study.
This represents a somewhat different use of agentic AI.
Rather than navigating an entire diagnostic workflow like MIRA, MoChiAgent coordinates several analytical components to work through complex longitudinal patient information.
That matters because healthcare data rarely fits into a single measurement.
A patient’s risk can depend on events occurring over months or years, with useful information distributed across laboratory results, diagnoses, medications and clinical encounters.
Agentic systems may be particularly useful when the task requires combining information from multiple sources rather than analysing a single scan or laboratory test in isolation.
The Important Difference Is Action
The growing interest in clinical agents reflects a broader change in how healthcare AI is being designed.
Most earlier AI systems handled a narrow task.
An imaging model might identify a suspicious area on a scan. A prediction model might estimate the probability of a specific condition. A language model might provide a written answer.
Agents add another layer.
They can decide which tool to use next.
That distinction changes both the potential value and the risk.
Consider a patient arriving with several symptoms.
A conventional model might produce a list of possible diagnoses.
An agent could theoretically gather additional history, choose necessary tests, inspect the results, update its reasoning, and determine whether further action is needed.
Each additional step gives the system more capability.
It also creates another point where something can go wrong.
Real Clinical Use Requires More Than Benchmark Accuracy
High scores on medical benchmarks help measure progress, but they are not enough to establish clinical safety.
Hospitals operate in environments where patient information can be incomplete, contradictory or entered incorrectly.
Clinical decisions can also depend on circumstances that are difficult to represent in a benchmark.
Researchers behind MIRA explicitly called for prospective real-world studies before concluding clinical deployment. The Nature Medicine work on selective autonomy similarly focused heavily on reliability rather than diagnostic accuracy alone.
That is likely to become one of the defining questions around agentic healthcare AI.
The issue is no longer simply whether the model can produce the correct answer.
It is whether the system can recognise uncertainty, operate within authorised boundaries, and reliably transfer responsibility to a human when necessary.
Hospitals May Need Agents That Can Be Governed Locally
The Nature Medicine study also highlights another emerging concern: where the AI system operates.
The researchers built their clinical agent for on-premises deployment, allowing a healthcare institution to maintain operational control over the model and its data environment.
That approach could matter for hospitals dealing with sensitive patient information.
Healthcare organisations may want stronger control over data handling, system updates, audit logs and the clinical actions an agent is permitted to perform.
The underlying AI model is therefore only one part of the system.
Hospitals would also need governance around permissions, monitoring, escalation and accountability.
An agent that can use clinical tools cannot simply be given unlimited access to every part of a hospital system.
Human Oversight Is Still Central to the Current Model
The latest research does not point toward hospitals removing clinicians from care.
It points toward varying levels of supervised autonomy.
ARPA-H’s ADVOCATE program includes a separate supervisory AI system and mechanisms for escalating care to healthcare professionals.
The Nature Medicine research examines selective autonomy, where uncertain cases are intentionally routed for human review.
MIRA was evaluated in a sandbox rather than deployed as an independent physician.
These differences matter when discussing autonomous healthcare AI.
Current research is not simply about making an AI system capable of doing more.
Researchers are also trying to determine when it should be permitted to act, how its behaviour should be monitored and when the system should stop.
Agentic AI Is Approaching a More Serious Clinical Test
Healthcare AI has spent years improving at recognising patterns, predicting outcomes and answering medical questions.
Agentic AI poses a harder challenge.
Can a system safely decide what information it needs, use the appropriate clinical tools, interpret the results and choose what should happen next?
MIRA shows that autonomous agents can simulate complex clinical workflow. Recent Nature Medicine research suggests reliability signals could help determine when an agent should defer to a human. MoChiAgent shows how multi-tool agents could work across longitudinal health records. And ARPA-H is now funding an effort designed specifically around a regulatory pathway for agentic cardiovascular care.
None of that means autonomous AI doctors have arrived.
It does mean the field is moving beyond demonstrations of what medical AI knows.
The next test is whether an AI system can be trusted with carefully defined clinical actions and whether it knows when not to take them.
What's Your Reaction?
 Like
0
 Dislike
0
 Love
0
 Funny
0
 Angry
0
 Sad
0
 Wow
0